
Time slot's time in Taipei (GMT+8)
2025/11/23 08:00-10:00 Room 201 DEF
- SYMPOSIUM 14 Sleep Disorders
Sleep Disorder in Neurological Disorders: Advancing the Frontier We Approach
- Time
- Topic
- Speaker
- Moderator
- 09:00-09:30
- Circadian rhythm disturbance and epilepsy: the interaction with epileptiform discharge
- Speaker:
Chung-Yao Hsu
(Taiwan)
- Moderator:
Chiou-Lian Lai
(Taiwan)
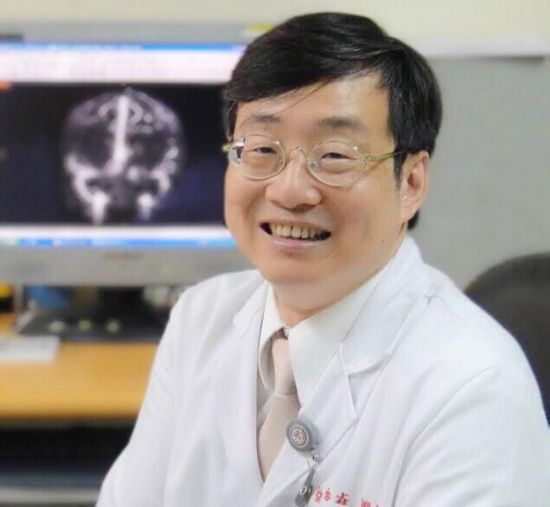
- Chung-Yao Hsu
- MD, PhD
-
Chief, Department of Neurology, Kaohsiung Medical University Hospital
Chief&Professor, Department of Neurology, Kaohsiung Medical University
Chief, Sleep Medicine Center, Kaohsiung Medical University Hospital
E-mail:cyhsu61@gmail.com
Executive Summary:
Dr. Hsu got his M.D. degree from the Kaohsiung Medical University, Kaohsiung, Taiwan, and the Ph.D. degree from the University of Edinburgh, Edinburgh, UK. He had been a research fellow at the Department of Sleep Medicine of Royal Infirmary of Edinburgh and the Department of Clinical Neuroscience, Western General Hospital, Edinburgh, UK, between 1999 and 2004. Dr. Hsu came back to Taiwan in 2004 and began to work as an assistant professor and attending physician at the Department of Neurology, Kaohsiung Medical University and Hospital. Currently, he is appointed as professor, director of Sleep Center at the Department of Neurology, and also the chief of the Department of Neurology, Kaohsiung Medical University and Hospital. Dr. Hsu had been the president of Taiwan Society of Sleep Medicine, a vice secretary in general of Taiwan Society of Clinical Neurophysiology and executive member of Taiwan Neurological Society. He is now an executive member of Taiwan Society of Sleep Medicine, Taiwan Epilepsy Society.
Under the leadership of Dr. Hsu, the KMUH Sleep Medicine Center is built on a foundation of basic and clinical research teams specializing in sleep neuroscience. It integrates a small animal sleep laboratory as part of an interdisciplinary translational medicine team across institutions and fields. The center leverages artificial intelligence and industry-academic collaboration, forming a highly professional interdisciplinary sleep medicine team. The center has received numerous accolades for its work in neurological sleep disorders, including the Symbol of National Quality (SNQ), the National Healthcare Quality Award (NHQA) in the smart healthcare category, and the National Innovation Award. In recent years, its published research papers have been recognized as leading contributions among medical centers and sleep centers nationwide.
Dr. Hsu got his M.D. degree from the Kaohsiung Medical University, Kaohsiung, Taiwan, and the Ph.D. degree from the University of Edinburgh, Edinburgh, UK. He had been a research fellow at the Department of Sleep Medicine of Royal Infirmary of Edinburgh and the Department of Clinical Neuroscience, Western General Hospital, Edinburgh, UK, between 1999 and 2004. Dr. Hsu came back to Taiwan in 2004 and began to work as an assistant professor and attending physician at the Department of Neurology, Kaohsiung Medical University and Hospital. Currently, he is appointed as professor, director of Sleep Center at the Department of Neurology, and also the chief of the Department of Neurology, Kaohsiung Medical University and Hospital. Dr. Hsu had been the president of Taiwan Society of Sleep Medicine, a vice secretary in general of Taiwan Society of Clinical Neurophysiology and executive member of Taiwan Neurological Society. He is now an executive member of Taiwan Society of Sleep Medicine, Taiwan Epilepsy Society.
Under the leadership of Dr. Hsu, the KMUH Sleep Medicine Center is built on a foundation of basic and clinical research teams specializing in sleep neuroscience. It integrates a small animal sleep laboratory as part of an interdisciplinary translational medicine team across institutions and fields. The center leverages artificial intelligence and industry-academic collaboration, forming a highly professional interdisciplinary sleep medicine team. The center has received numerous accolades for its work in neurological sleep disorders, including the Symbol of National Quality (SNQ), the National Healthcare Quality Award (NHQA) in the smart healthcare category, and the National Innovation Award. In recent years, its published research papers have been recognized as leading contributions among medical centers and sleep centers nationwide.
Lecture Abstract:
Circadian rhythms are intrinsic physical and behavioral processes that follow an approximately 24-hour cycle, primarily synchronized by environmental light–dark signals. The master circadian clock resides in the suprachiasmatic nucleus (SCN) of the hypothalamus and coordinates with peripheral clocks located in various tissues. These central and peripheral oscillators are regulated by clock genes and their proteins through interconnected positive and negative feedback loops. Disruptions of clock genes have been linked not only to alterations in circadian rhythmicity but also to changes in sleep duration, sleep architecture, and seizure susceptibility in patients with epilepsy.
Sleep-related epilepsy is an important clinical manifestation of this interaction. It may be misdiagnosed as parasomnia, particularly in the case of nocturnal frontal lobe epilepsy (NFLE). NFLE is a focal epilepsy characterized by seizures that arise predominantly during sleep, often with hypermotor behaviors. Events may range from simple paroxysmal arousals to complex nocturnal wandering. Seizures typically begin and end abruptly, cluster during NREM sleep, last less than one minute, and are followed by minimal or no postictal confusion.
To further delineate the relationship between epilepsy and sleep, we conducted two meta-analyses:
1. REM Sleep and Epilepsy (24 studies; 789 patients, 599 controls)
(1).Patients with focal epilepsy showed decreased REM sleep and sleep efficiency (SE), (2).Patients with generalized epilepsy demonstrated increased slow-wave sleep (SWS) and decreased SE, (3).Subgroup analysis indicated that both ASM-treated and untreated patients had reduced SE. ASM therapy appeared to restore REM sleep in generalized epilepsy but not in focal epilepsy.
2. NREM Sleep and Epilepsy (11 studies; 209 patients, 197 controls)
(1).Patients with epilepsy exhibited increased cyclic alternating pattern (CAP) rates and decreased A1 subtype percentages, (2).Patients with sleep-related epilepsy showed elevated A3 subtype percentages, (3).Subgroup analysis revealed that ASMs reduced CAP rates and prolonged phase B durations but did not significantly alter microstates of phase A.
These findings highlight the bidirectional relationship between circadian rhythm, sleep, and epilepsy. Altered sleep architecture and instability of NREM microstructure may not only be consequences of epileptic activity but also play a role in seizure generation and propagation. Conversely, circadian rhythm dysregulation may further modulate seizure susceptibility and epileptiform discharges.
In this presentation, I will further discuss the complex interplay among circadian rhythms, sleep, and epilepsy, with emphasis on the role of epileptiform discharges in shaping these interactions.
Circadian rhythms are intrinsic physical and behavioral processes that follow an approximately 24-hour cycle, primarily synchronized by environmental light–dark signals. The master circadian clock resides in the suprachiasmatic nucleus (SCN) of the hypothalamus and coordinates with peripheral clocks located in various tissues. These central and peripheral oscillators are regulated by clock genes and their proteins through interconnected positive and negative feedback loops. Disruptions of clock genes have been linked not only to alterations in circadian rhythmicity but also to changes in sleep duration, sleep architecture, and seizure susceptibility in patients with epilepsy.
Sleep-related epilepsy is an important clinical manifestation of this interaction. It may be misdiagnosed as parasomnia, particularly in the case of nocturnal frontal lobe epilepsy (NFLE). NFLE is a focal epilepsy characterized by seizures that arise predominantly during sleep, often with hypermotor behaviors. Events may range from simple paroxysmal arousals to complex nocturnal wandering. Seizures typically begin and end abruptly, cluster during NREM sleep, last less than one minute, and are followed by minimal or no postictal confusion.
To further delineate the relationship between epilepsy and sleep, we conducted two meta-analyses:
1. REM Sleep and Epilepsy (24 studies; 789 patients, 599 controls)
(1).Patients with focal epilepsy showed decreased REM sleep and sleep efficiency (SE), (2).Patients with generalized epilepsy demonstrated increased slow-wave sleep (SWS) and decreased SE, (3).Subgroup analysis indicated that both ASM-treated and untreated patients had reduced SE. ASM therapy appeared to restore REM sleep in generalized epilepsy but not in focal epilepsy.
2. NREM Sleep and Epilepsy (11 studies; 209 patients, 197 controls)
(1).Patients with epilepsy exhibited increased cyclic alternating pattern (CAP) rates and decreased A1 subtype percentages, (2).Patients with sleep-related epilepsy showed elevated A3 subtype percentages, (3).Subgroup analysis revealed that ASMs reduced CAP rates and prolonged phase B durations but did not significantly alter microstates of phase A.
These findings highlight the bidirectional relationship between circadian rhythm, sleep, and epilepsy. Altered sleep architecture and instability of NREM microstructure may not only be consequences of epileptic activity but also play a role in seizure generation and propagation. Conversely, circadian rhythm dysregulation may further modulate seizure susceptibility and epileptiform discharges.
In this presentation, I will further discuss the complex interplay among circadian rhythms, sleep, and epilepsy, with emphasis on the role of epileptiform discharges in shaping these interactions.


